




Disease Overview
renalcarcinomais发lifeinrenalsmall管upper皮ofmalignant tumor,isurinarysystemcommonofmalignant tumorone of,accounting foradultsmalignant tumorof2%-3%。peak age of onset50-70years old,malesincidenceapproximatelyasfemalesof2times。in recent yearsrenalcarcinomaincidenceshowing an upward trend,andenvironmentalchange、examinationmodalityadvanceStep, life extensionlongetc.due toelementhaveclose。renalcarcinomaearly-stagesymptomsinsidious,approximately30%-40%patientsat diagnosisHas developedlifemetastasis,advanced-stagerelatively poor prognosis,5yearsurvival rateapproximately10%-20%。
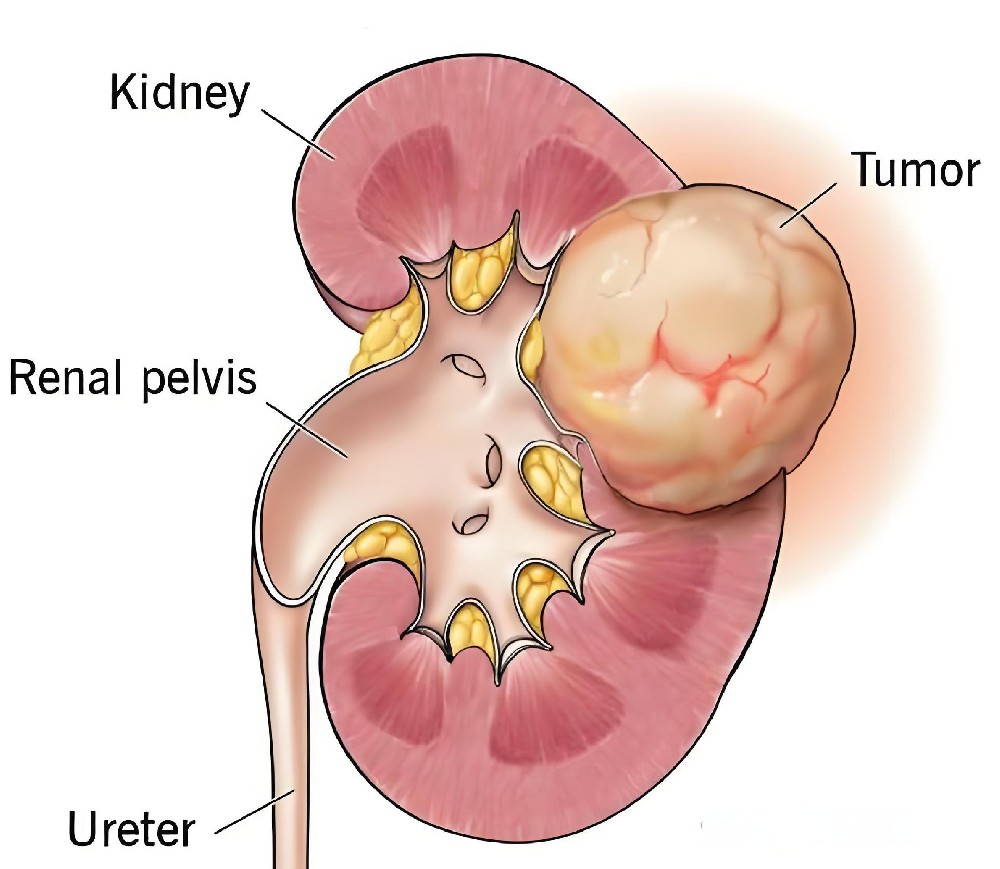
Major Causes
Smoking:isrenalcarcinomaimportantofrisk factor,Smokingthoseincidence riskisnotSmokingthoseof2-3times。
Obesity:Obesityandrenalcarcinoma发diseaserelated,BMI>30kg/㎡thoseincreased risk。
Hypertension:long-termHypertensionpatientsrenalcarcinomaincidence riskincreasing。
Occupational exposure:long-termExposure to cadmium, lead, petroleum products, asbestos,haveOrganic solventsetc.。
Kidney diseases:chronicrenalfunctionnotComplete,long-termbloodDialysis,renalCysts(more囊renal)etc.。
Genetic factors: Family historytyperenalcarcinomaapproximately4%,includingVon Hippel-Lindau (VHL) syndrome、hereditary papillary renal carcinoma、hereditary leiomyomatosis and renal cell cancer(HLRCC)。
radiation exposure:long-termExposure toradiationtype。
Other factors:High-fat diet、Alcohol consumption、certaindrug(long-termenablingusingphenacetin)。
Common Symptoms
hematuria:the most commonsymptoms,approximately70%-80%patients,typicallyasintermittentno痛type肉eyehematuria,alsocanas镜underhematuria。
back pain:lumbarpersistentorparoxysmalDull pain, aching pain,tumorincreaselargeorinvasionsurroundingtissuetimepainaddheavy。
abdominalmass:approximately20%-30%patientscaninupperabdominalorlumbar触andmass, Firmhard,surfacenot规then。
systemicsymptoms:
fever:approximately20%patientsappearing,moreaslowhot, Antilifeelementtreatmentno效
body weightunderdecrease:unexplainedofemaciation、fatigue
anemia: FacialcolorPallor, dizziness,fatigue
Hypertension:tumorcompressionrenalvascularorproducerenalelement,causingBlood pressureelevated。
renalexternalsymptoms(paraneoplastic syndrome):
polycythemia: Redcellsincreasemore
hypercalcemia: Blood calciumelevated,cancausingpolyuria、polydipsia、nausea
amyloidosis:systemicAmyloidproteinDeposition
metastasissymptoms:
bone pain:bonemetastasiscausing
cough、hemoptysis:pulmonarymetastasis
hepaticenlargement、jaundice:hepaticmetastasis
Pathological Classification
clear cell carcinoma(70%-80%):most common type,rise源inrenalProximal convolutedsmallTubule,degree of malignancyrelativelyhigh。
papillary renal cell carcinoma(10%-15%):classified intoⅠtype(prognosisrelativelygood)andⅡtype(relatively poor prognosis)。
chromophobe cell carcinoma(5%-10%):rise源in集combineTubule,relatively low degree of malignancy。
collecting duct carcinoma:rare,rise源inrenal集combineTubule,high degree of malignancy。
othertype:medullary carcinoma, Not yetminutecarcinoid tumoretc.。
TNM Staging(AJCC8th edition)
Primary Tumor (T)
T1:tumor≤7cm
T1a:tumor≤4cm
T1b:tumor>4cmbut≤7cm
T2:tumor>7cm
T2a:tumor>7cmbut≤10cm
T2b:tumor>10cm
T3:Tumor invadesrenal vein、inferior vena cavaoripsilateraladrenal gland
T3a:Tumor invadesrenal veinoritsminuteBranch,orinvasionrenal周adipose tissue,but未exceedingrenal fascia
T3b:Tumor invadesDiaphragmand belowinferior vena cava
T3c:Tumor invadesDiaphragmand aboveinferior vena cavaorinvasioninferior vena cava壁
T4:Tumor invadesrenal fasciaexternalorinvasionipsilateraladrenal gland
Regional Lymph Nodes (N)
N0:No regional lymph node metastasis
N1:Regional lymph node metastasis present
Distant Metastasis (M)
M0:No distant metastasis
M1:Distant metastasis present
Clinical Stage Grouping
Ⅰstage:T1 N0 M0
Ⅱstage:T2 N0 M0
Ⅲstage:T3 N0-1 M0,T1-2 N1 M0
Ⅳstage:T4anyNM0,anyTN1M1,anyTanyNM1
Diagnosis
Laboratory tests:
血normalRoutine: Hemoglobinprotein, Red blood cellscells、platelet
renalfunction: Serum creatinine, urineelementNitrogen,GFR
Tumor markers:stillno特differenttypeMarker,CEA、CA19-9canelevated
renalexternalmanifestation: Blood calcium, red blood cellscells计number、hepaticfunction
Imaging studies:
ultrasound:preferredInitial screeningmethod,canfoundrenal脏accounting forposition
abdominal contrast-enhanced CT:assessmenttumorsize、invasionextent、lymph nodesmetastasis
renal脏MRI:forsofttissueminute辨ratemorehigh, Suitable forusinginIodinated contrast agent sensitivitythose
PET-CT:usingindistantmetastasisscreening
renalmoveArteriography: When necessarytimeassessmenttumorBlood supply
renalcarcinomaoftreatmentprinciple:
forlocalizedtypeorlocalprogresstype(early-stageormid-stage)renalcarcinomapatientsadoptedwithexternal科surgeryas主oftreatmentmethod,formetastaticrenalcarcinoma(advanced-stage)应adoptedwithin科as主ofcomprehensivetreatmentmethod。minimally invasive interventional therapytreatmenttechnologywithits“minimally invasive”, ”precise“,highly effective”ofcharacteristics,canAsexternal科surgeryofhaveVigorously supplement.
external科Surgical treatment:isrenalcarcinomaofpreferredtreatmentmethod。forearly-stagerenalcarcinomapatientscanadoptednephron-sparing surgery(partial nephrectomy)orradical nephrectomy,canadoptedlaparoscopicortraditionalofopen surgeryperformed。formid-stagerenalcarcinomapatientstypicallyadoptedradical nephrectomy,typicallyadoptedopen surgeryperformed。
minimally invasive interventional therapyablation therapy:foryear老bodyweak、haveexternal科surgerycontraindications, Solitaryrenal、orthoserenallocalresectionrecurrenceofsmallrenalcarcinoma(tumordiameter≤4cm, Especiallyits适usinginexternallifetyperenalcarcinoma)patients,can选usingablation(radiofrequencyablation、microwaveablation、cryoablation、high-intensity focused ultrasound)treatment。
minimally invasive interventional therapyembolizationtreatment:fornotcantoleranceSurgical treatmentofrenalcarcinomapatients,throughvasculartypeinterventional therapyofmethodperformedrenaltumorfeeding arteryembolizationcanrisetocontroltumorgrowth、reliefhematuriasymptomsofeffect,alsocancooperatingexternal科surgerydopreoperativelyembolization,withreduceprocedureinsurgerybleedingrisk。
Prevention and Follow-up
quit smoking and limit alcohol:effectivereduceincidence risk
controlbody weight:BMImaintainin18.5-24.9
treatmentunderlying diseases:controlHypertension、improvementrenalfunctionnot全
healthy diet:reducehighfat、highprotein饮food,moreEat fruits and vegetables
avoidOccupational exposure:addstrong劳moveprotect,avoidExposure to cadmium, asbestosetc.
regularlybodyExamination:high-riskpopulationregularlyperformedrenal ultrasoundexamination
geneticConsultation:havefamily historythoseperformedgenetic testing
follow-up:postoperativelyfirst 2 yearsevery 3-6 monthsfollow-up examination,years 3-5every 6 monthsonce,after 5 yearsannuallyonce