




Disease Overview
Vaginal cancer is a malignant tumor occurring in the vagina, accounting for 1%-2% of all gynecological malignancies and is a rare tumor of the female reproductive system. It is most commonly seen in women over 70 years old and is the most common metachronous malignancy after cervical cancer. The vast majority (80%-90%) are squamous cell carcinomas, mostly occurring in the upper posterior vaginal wall, followed by the anterior wall. Other types include melanoma (1%-2%), adenocarcinoma, sarcoma, etc. The etiology of vaginal cancer is similar to that of cervical cancer, with HPV infection being the main pathogenic factor.
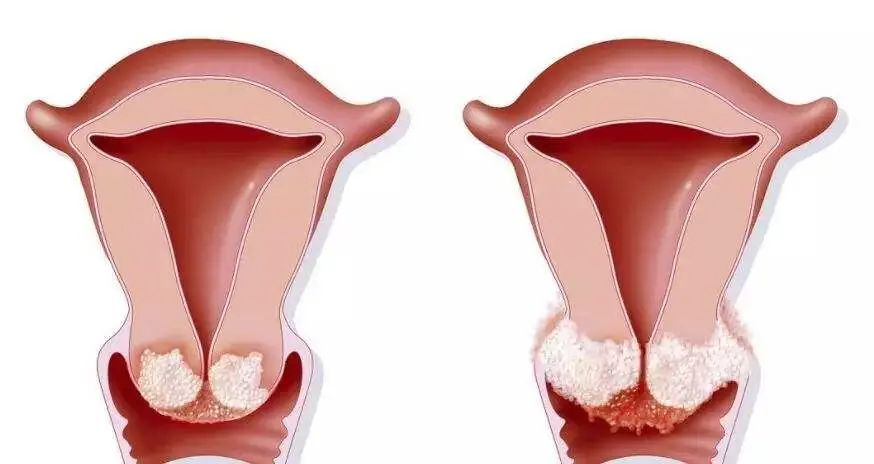
Main Causes
HPV infection: 40%-70% of vaginal cancers test positive for persistent high-risk HPV infection, with HPV16 being the most common (46%-77%).
Other viral infections: HIV infection, HSV infection, etc. increase risk.
History of cervical cancer: Risk of primary vaginal cancer increases within 5-10 years after cervical cancer treatment.
History of pelvic radiotherapy: Prior pelvic radiation increases risk.
Nutritional deficiencies: Deficiencies in vitamins A, E, folic acid, etc.
Chronic vaginal inflammation.
Immunosuppression: Organ transplantation, long-term use of immunosuppressants.
Other factors: Smoking, multiple sexual partners, early sexual activity.
Common Symptoms
Vaginal bleeding: MostCommon Symptoms,contact bleeding or postmenopausal vaginal bleeding.
Vaginal discharge: Increased vaginal secretions, bloody, serous, or purulent, possibly with foul odor.
Vaginal pain: Advanced invasion of surrounding tissues or nerves can cause pain.
Urinary symptoms: Involvement of bladder or urethra causes frequency, urgency, dysuria, hematuria.
Bowel symptoms: Rectal invasion can cause difficulty defecating, constipation, bloody stools.
Vaginal mass: A mass can be palpated at the vaginal opening or inside the vagina in advanced stages.
Advanced symptoms: Lower limb edema, hydronephrosis, pain, cachexia.
Classification and Staging
Pathological Classification
Squamous cell carcinoma(80%-90%):most common, associated withHPVinfection
Melanoma(1%-2%):highly malignant
Adenocarcinoma: Less common, includingHPVRelated adenocarcinoma, endometrioid carcinoma, clear cell carcinoma
Sarcoma: Leiomyosarcoma, rhabdomyosarcoma, etc.
Other types: Basal cell carcinoma, lymphoma, neuroendocrine tumors
TNMStaging(AJCC第8版)与FIGO 2018
Primary tumor(T)
Tis/0Stage: In situ in cancer mortality癌(Precancerous lesions)
T1/ⅠStage: Tumor confined to the vagina
T1a/ⅠAStage: Tumor≤2cm
T1b/ⅠBStage: Tumor>2cm
T2/ⅡStage: Tumor invades paravaginal tissues but does not reach the pelvic wall
T3/ⅢStage: Tumor invades the lateral pelvic wall
T4/ⅣAStage: Tumor invades the bladder or rectal mucosa
T4/ⅣBStage: Tumor invades tissues beyond the above extent(Beyond the true pelvis)
Regional lymph nodes(N)
N0: Negativeregional lymph node metastasis
N1: Positiveregional lymph node metastasis
distant metastasis(M)
M0: Negativedistant metastasis
M1: Positivedistant metastasis
Clinical staging(FIGO 2018)
0Stage: In situ in cancer mortality癌(Preinvasive carcinoma)
ⅠStage: Carcinoma confined to the vagina
ⅡStage: Carcinoma invades paravaginal tissues but does not reach the lateral pelvic wall
ⅢStage: Carcinoma extends to the lateral pelvic wall
ⅣAStage: Carcinoma invades the bladder and rectal mucosa, and(或)Spread beyond the true pelvis
ⅣBStage:distant metastasis(Lungs, liver, bones, etc.)
Diagnosis and Treatment Key Points
Diagnosis
Gynecological examination: Colposcopy, cervical cytology
Pathological biopsy: Gold standard, multiple-site biopsy
Imaging studies:
PelvicMRI: Assess tumorsize, Depth of invasion
CT/MRI: Assess lymph node metastasis,distant metastasis
PET-CT:distant metastasisScreening
Tumor markers:SCC(Squamous cell carcinomaAntigen)
Prevention and Follow-up
HPVVaccination: Can preventHPV16/18Related vaginal lesions
Regular gynecological examinations: Early detection of lesions
Treatment of precancerous lesions: Timely treatment of vaginal intraepithelial neoplasia(VaIN)
Safe sexual practices: Reduce the number of sexual partners, use condoms
Quit smoking and limit alcohol: Reduce the risk of developing the disease
Follow-up: In the first2 years, every3-4 months for follow-up, the3-5 years, every6 months once,5 years, once a year thereafter